
The challenges facing spine surgery
Spine surgery is still defined by misplaced screws, radiation, lost OR time, and high costs — risks no tool has yet solved.

0mm
pedicle corridor diameter
Why millimeters matter
The pedicle corridor is narrow. A single millimeter off course can mean the difference between a safe placement and serious complications.
Whatever your challenge — patient safety, surgeon safety, learning-curve or surgical efficiency — if it matters to you, we've built the solution.
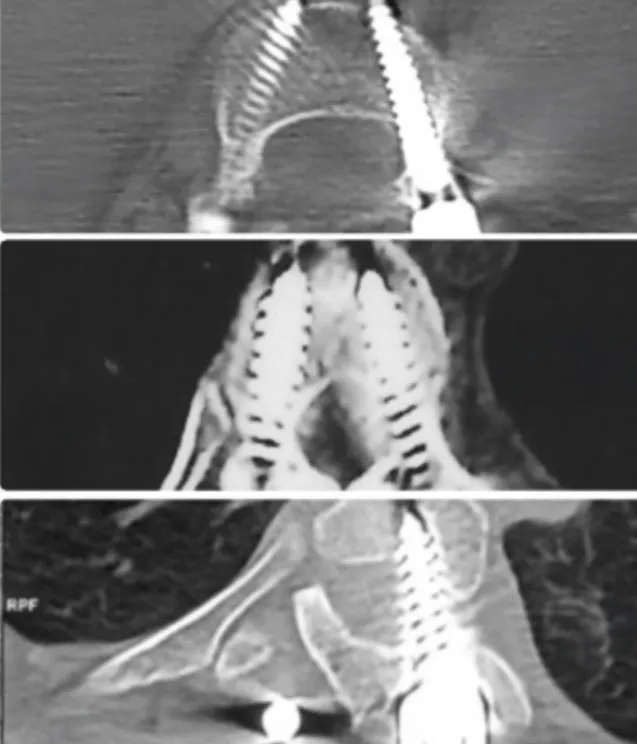
Pedicle screw malalignment

"Do no harm"
Sokrates
But unfortunately, harm is done on occasion
- Spinal cord injuries and neurological damage
- Major vascular perforations
- Mechanically unstable constructs
- Extended hospital stays and patient suffering
With 6.5 million pedicle screws placed annually worldwide, even small error rates translate into enormous human and financial impact.
Navigation and robotic systems are not immune — intraoperative revisions due to misplacement reach 8.1–12.9% for navigation and 2.3–8.8% for robotics. Post-operative revision rates remain 0.9–1.35% for navigation and up to 1.0% for robotic-assisted procedures.
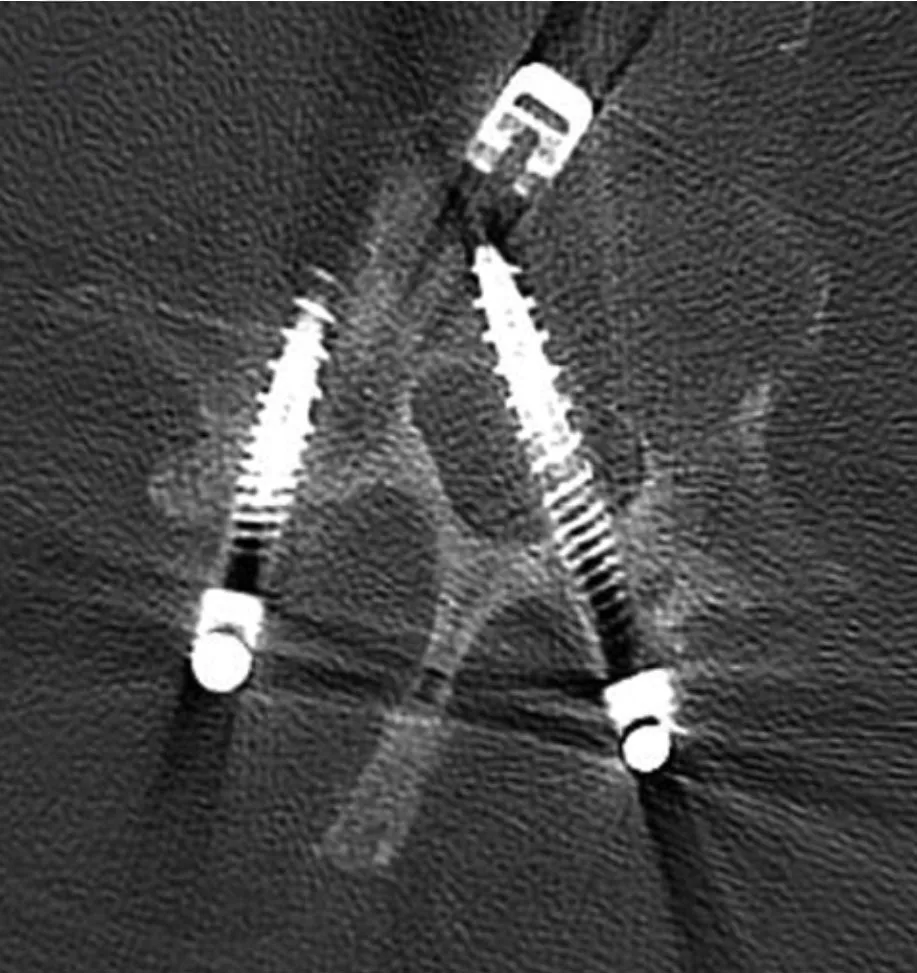
8–13%
intraoperative revisions
due to misplacement with navigation systems
0.8–12.2%
freehand post-operative revision rate

$1.5B
annual revision expenditure in the USA alone
Excessive radiation exposure
Flooding the OR with X-rays and CT scans for screw checks is a dangerous and somewhat dated habit — putting surgeons, staff, and patients at needless risk of radiation damage. Surely, there's a smarter way…
For OR team:
- Cumulative radiation exposure drives cancer, cataracts, thyroid disease
- Lead aprons are heavy, exhausting
For the patient:
- Pediatric patients face higher lifetime risk
Navigation and robotics shift radiation from surgeon to patient. Intraoperative CT delivers 3–10× higher doses than fluoroscopy — hundreds of chest X-rays in one case.
Staff are safer, but patients — especially the young — face unnecessary long-term cancer risk.

Spine surgeons face a
0×
greater cancer risk
Cumulative exposure often exceeds lifetime dose limits — even when annual levels appear compliant.
Surgeon exposure
µSv per procedure
Patient exposure
µSv per procedure
Workflow interruptions
Surgeons face relentless pressure to operate faster, turn cases around quicker, and maximize OR throughput — yet every unnecessary delay makes that impossible.
Technology can disturb workflow
- Frequent C-arm repositioning interrupts surgical workflow and may increase risk of infections
- Long setup time of CAS systems wastes OR minutes
- Requires extra staff/technicians where staff shortages are the norm
- Unfavorable ergonomics for surgical team
- One patient shift requires recalibration of CAS systems
0
hrs/month wasted on setup alone
0
extra surgeries per month possible
* Drape, boot, register, plan, arm positioning (15–25 min) — 4 spine surgeries/week
The last millimeters: The look-ahead challenge
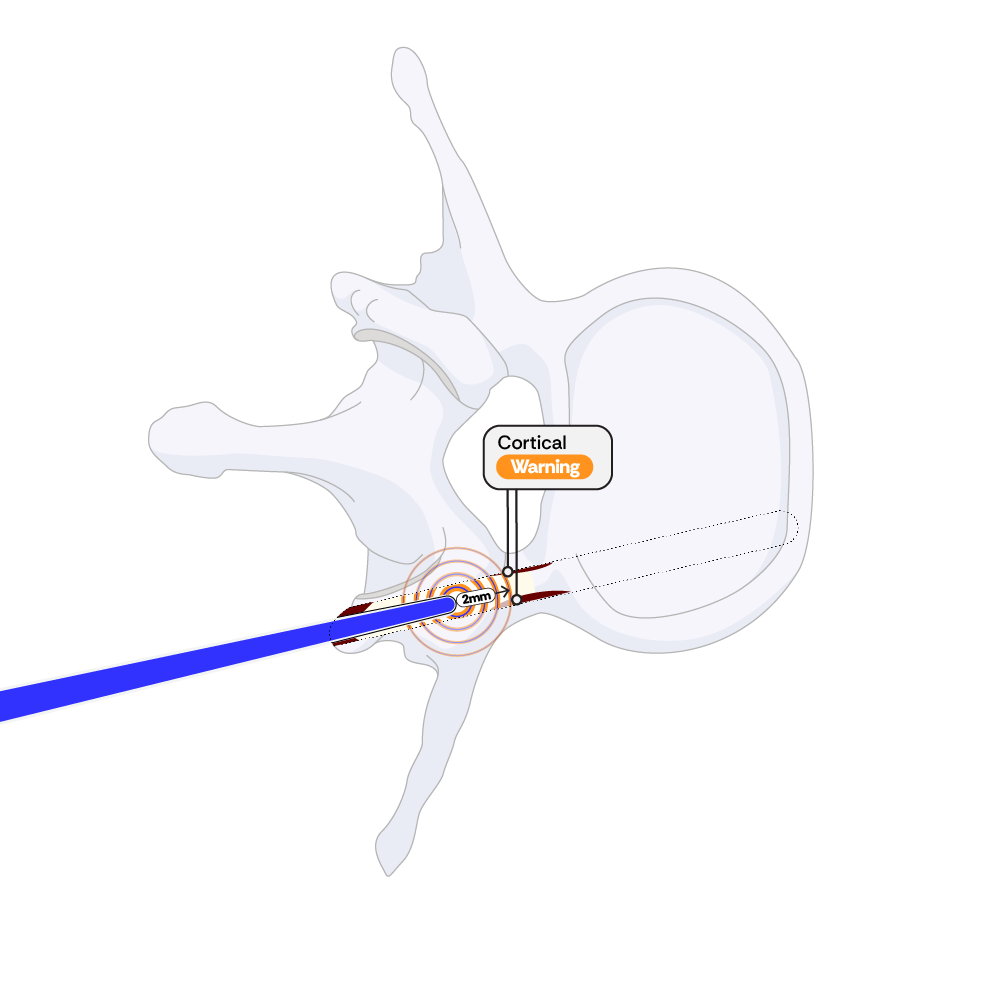
Pedicle screw placement is a game of millimeters. Accuracy in the critical zone before cortical breach separates safe fixation from nerve injury, revision surgery, or worse.
Why it's a problem
Freehand techniques
Surgeons rely on feel and fluoroscopy. Neither provides reliable warning in the last millimeters.
Navigation and Robots
These systems project planned trajectories from imaging. But once the spine shifts, the screen may not reflect reality. They do not sense bone quality in real time.
Dynamic Surgical Guidance (DSG)
The DSG probe listens for changes in electrical conductivity, but only at the tip. Feedback comes too late — when a breach may already be unavoidable.
Prohibitive capital investment barriers
Navigation and Robotic systems reduce complication rates to between 0.7% and 0.9%; however, they require sizeable upfront investment, and have high annual maintenance costs.
It's not all roses...
- Prohibitive capital investment costs
- High annual recurring running costs
- Modest absolute risk reduction in relation to costs
- Loss of surgeon autonomy & erosion of surgeon skill
- Radiation trade-offs: less surgeon exposure, much higher patient exposure
Global costs for revision surgeries and complications continue to rise — a burden shared by patients, hospitals, and healthcare systems alike.
Ready for the solution?
See how it works